
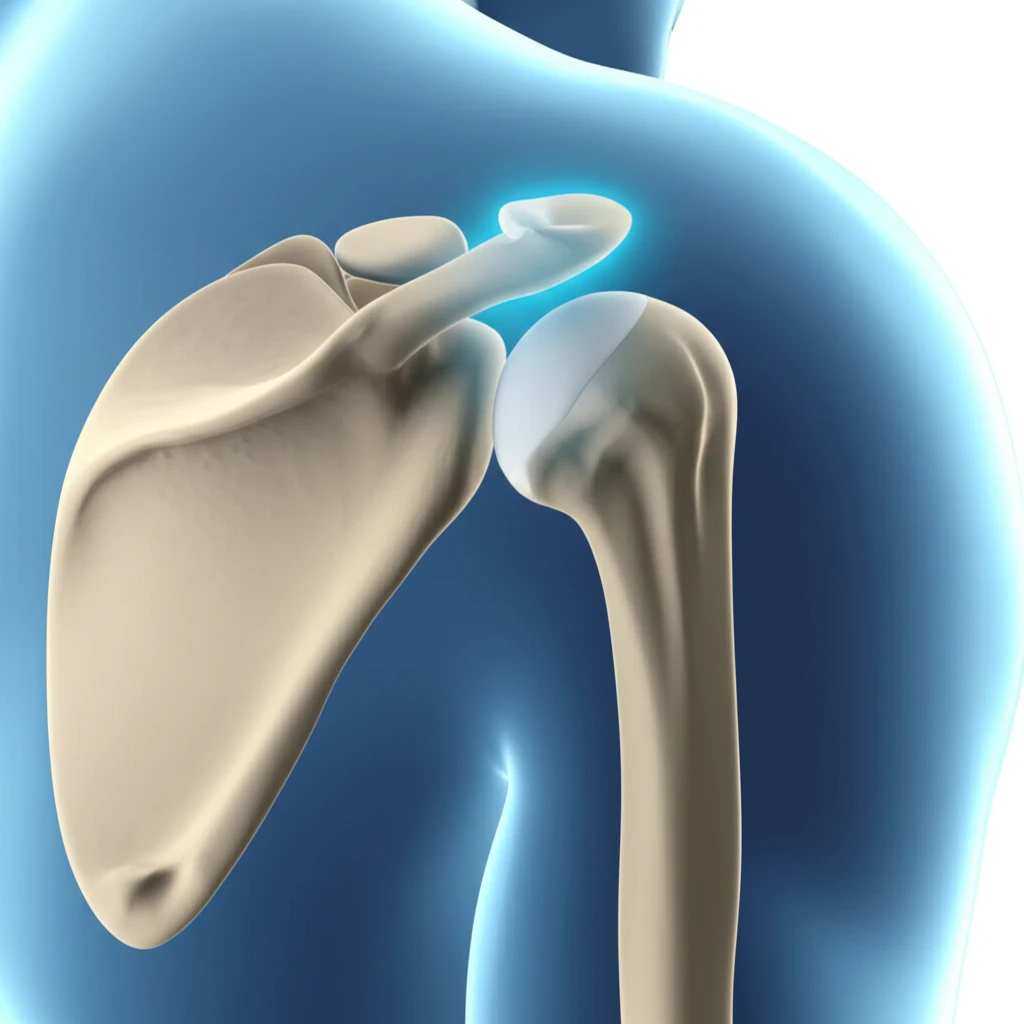
Decoding Shoulder Pain: Is Your Acromioplasty Site the Key to Recovery?

"A new study reveals how the precise location of acromioplasty can significantly impact outcomes for shoulder impingement and rotator cuff repair."
Shoulder pain can be a frustrating and debilitating experience, especially when it stems from rotator cuff tears or shoulder impingement. For many, acromioplasty – a surgical procedure to reshape the acromion bone – offers a potential solution. However, recent research suggests that the success of acromioplasty may hinge on a critical detail: the specific location where the bone is reshaped.
Traditionally, a large critical shoulder angle (CSA) has been linked to an increased risk of rotator cuff tears. Acromioplasty aims to reduce this angle, theoretically preventing tears or minimizing the risk of re-tears after surgical repair. But which part of the acromion should surgeons target to achieve the best results? This question has remained a subject of ongoing investigation.
A new anatomical study sheds light on this critical question, revealing that the site of acromioplasty significantly influences the reduction of the CSA. By understanding the individual anatomical variations of the scapula (shoulder blade), surgeons can tailor their approach for more effective and consistent outcomes. Let's delve into the key findings of this study and explore how they could revolutionize shoulder pain treatment.
Diagnosis and treatment considerations
Subacromial impingement syndrome can present with shoulder pain and reduced strength, but rotator cuff tears and long-head biceps tears are also possible causes of those symptoms. In the Cochrane source’s example, ultrasound was used to confirm the impingement diagnosis while excluding a full-thickness rotator cuff tear and other differential diagnoses. Rotator cuff tears are reported to affect 30–50% of people over age 50 and are a common cause of function-limiting shoulder pain and weakness. These overlapping symptoms make identifying the underlying condition an important part of evaluating shoulder pain.
Acromioplasty: Location Matters
The study, led by Dominik Kaiser and colleagues, sought to determine the optimal location for acromioplasty to achieve the desired CSA reduction. Using eight scapulae with diverse anatomical characteristics, the researchers investigated the impact of both anterolateral and strict lateral acromioplasty on CSA reduction. The study first examined the influence of radiographic projection and then the effects of anterolateral versus strict lateral AP. Key to the study was the effect of scapular anatomy on outcomes.
- Lateral AP Superiority: Lateral acromioplasty of 5/10mm reduced the CSA significantly more than anterolateral AP of 5mm/10mm.
- Anatomical Variance: Depending on scapular anatomy, anterolateral AP did not alter CSA at all.
- Consistency: Consistent reduction of the CSA could be achieved by lateral AP in all eight scapulae.
Acromion shape, angle, and surgical approach
A systematic review and meta-analysis on critical shoulder angle (CSA) reported an anatomical study finding that lateral acromioplasty reduced CSA more than anterolateral acromioplasty. A separate review describes a proposed practical benefit of combining acromioplasty with arthroscopic rotator cuff repair: expanding the arthroscopic field of vision and working space, which may help with fixation of rotator cuff suture bridges. A 2026 article on anterior acromion extension notes that an acromion index increase or a CSA greater than 35 degrees has been highlighted as a risk factor for rotator cuff injuries.
Limits and causes of persistent symptoms
An anatomical study of acromioplasty sites identifies a key limitation: the real biomechanical effect produced by each procedure is not known. Recurrent tears after rotator cuff repair are common, and conservative care as well as open and arthroscopic revision procedures have been advocated for managing these failures. Johns Hopkins Medicine identifies ongoing recovery from surgery and shoulder stiffness from lack of movement as the most common causes of pain after rotator cuff surgery. These sources point to uncertainty about procedure-specific biomechanics and to recovery or repair failure as possible contributors to ongoing symptoms.
Personalized Approaches for Better Outcomes
The study underscores the importance of considering individual scapular anatomy when planning acromioplasty. For surgeons, this means moving towards a more personalized approach that takes into account factors like acromial slope, external rotation, and the location of the critical acromial point. Precise pre-operative planning and assessment can help determine whether a lateral or anterolateral approach is most appropriate for each patient.
Innovation and market outlook
A market report says the global rotator cuff repair market was valued at USD 848.2 million in 2023 and describes growth driven by established surgical techniques alongside newer orthobiologic and implant-based innovations. It also notes that regional dynamics and cost considerations influence adoption. Another source describes surgical techniques, implant materials, and patient-management strategies as areas shaping the market’s future trajectory. These materials describe market and technology trends, rather than establishing clinical outcomes for any particular innovation.
For patients, the research highlights the value of seeking out surgeons who are knowledgeable about these nuances and utilize advanced imaging techniques to assess their individual anatomy. Open communication with your healthcare provider is crucial to ensure that the chosen surgical approach aligns with your specific needs and anatomical characteristics.
Ultimately, by embracing a more tailored and anatomically-informed approach to acromioplasty, we can strive for more consistent and successful outcomes in the treatment of shoulder pain and rotator cuff disorders. Future research should focus on refining these techniques and developing even more precise methods for pre-operative assessment and surgical planning.