
Mysterious Ear Marks: The Connection Between Skin, Autoimmunity, and Your Health

"Unveiling the Hidden Signs of Anti-MDA5 Dermatomyositis and What It Means for Early Diagnosis and Treatment"
Have you ever noticed unusual marks or discoloration on your ears? What might seem like a minor cosmetic issue could actually be an important clue about your overall health. In the world of autoimmune diseases, early detection is crucial, and sometimes, the body provides subtle signals that can lead to timely intervention.
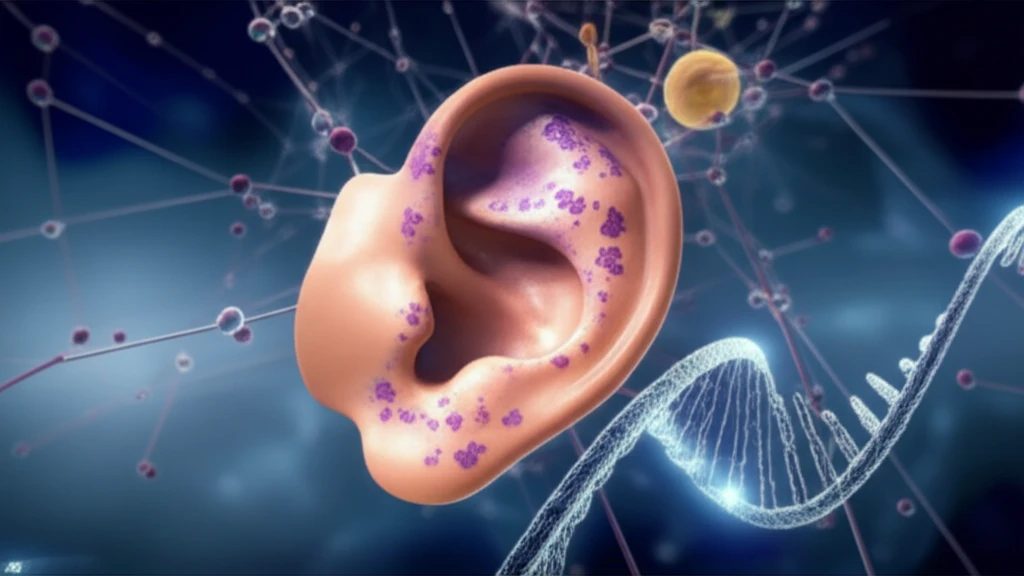
This article explores the connection between violaceous macules (small, purplish spots) on the antihelix and helix of the ear and anti-melanoma differentiation-associated protein 5 (MDA5) antibody-associated dermatomyositis. This condition is a type of autoimmune disease that affects the skin and muscles and can be associated with severe complications like rapidly progressive interstitial lung disease (RP-ILD).
We'll break down the research, explain the importance of recognizing these signs, and provide insights into what this could mean for those at risk. Whether you're a healthcare professional or someone keen on staying informed about your health, this guide will equip you with essential knowledge about this intriguing link.
Current Statistics and Impact
Dermatomyositis is a rare inflammatory myopathy marked by characteristic skin manifestations and variable muscle and systemic involvement. Recent U.S. population-based data cited by Science Insights estimate prevalence at about 13 per 100,000 people, or roughly 34,000 Americans, with approximately 2,858 new cases diagnosed annually and an incidence rate of 1.1 per 100,000. Clinical presentations range from muscle-predominant disease to amyopathic forms, while the Autoimmune Registry describes dermatomyositis as an uncommon autoinflammatory disease mainly affecting the skin and muscles.
Approach and Limitations
Dermatomyositis evaluation generally requires attention to both skin findings and possible muscle or systemic involvement. Because the disease can appear with muscle-predominant, skin-predominant, or amyopathic features, no single presentation captures every case. Diagnosis and management may therefore be complex, and medical assessment is needed to distinguish overlapping clinical patterns.
Historical Milestones
A historical account traces an early description to Professor Hans Unvericht, who in 1887 reported a peculiar muscle disease involving fatigue, malaise, muscle pain and weakness, facial swelling, and bluish eyelid lesions. In 1916, Stertz was reported as the first to describe an association between dermatomyositis and malignancy. In 1975, Anthony Bohan and James B. Peter classified polymyositis and dermatomyositis into five subtypes, a framework used for decades.
What Are Violaceous Macules and Why Do They Matter?
Violaceous macules are small, discolored spots that appear purplish or reddish-purple on the skin. They are different from typical blemishes or age spots, often indicating underlying vascular or inflammatory processes. In the context of autoimmune diseases like dermatomyositis, these macules can be significant diagnostic markers.
- Early Detection: Recognizing these macules can lead to quicker diagnosis.
- Treatment: Early treatment can significantly improve outcomes.
- Risk Awareness: Helps identify individuals at higher risk for complications like RP-ILD.
Latest Research and Reviews
Recent reviews describe dermatomyositis as a systemic autoimmune disease in which hallmark skin manifestations may accompany inflammatory myopathy and multisystem involvement. Newer classification approaches include skin-predominant subtypes and examine relationships between clinical phenotypes and myositis-specific autoantibodies. These developments have contributed to new treatment strategies and more integrated diagnostic approaches, while reviews continue to emphasize morbidity and the established risk of underlying malignancy.
Unresolved Challenges
Dermatomyositis does not follow a single predictable clinical course. Skin disease may occur with muscle involvement or, in some patients, without clinically apparent muscle disease, making broad assumptions about presentation unreliable. These variations can complicate diagnosis, classification, treatment selection, and assessment of disease activity.
Comparing Related Conditions
Comparisons between dermatomyositis and cutaneous lupus erythematosus emphasize overlap as well as differences in clinical presentation, pathogenesis, therapy, and complication risk. Dermatomyositis may feature Gottron’s sign, Gottron’s papules, and heliotrope rash, either with muscle weakness in classic disease or independently in clinically amyopathic disease. Assessment tools for cutaneous lupus and dermatomyositis include provider measures, patient-reported outcomes, and biomarkers, while the heterogeneity of amyopathic dermatomyositis makes definitive therapeutic and follow-up recommendations difficult.
The Future of Early Diagnosis
The identification of antihelix/helix violaceous macules as a characteristic sign of anti-MDA5 antibody-associated dermatomyositis marks a significant step forward in early diagnosis. Further research and broader awareness among healthcare professionals are essential to translate these findings into improved patient care. Keep an eye on your skin, and don't hesitate to seek medical advice if you notice anything unusual. Early detection is key to managing autoimmune conditions and maintaining your overall health.
Integrated Perspective
Dermatomyositis is best understood as a condition in which skin findings can be an important part of a broader autoimmune disease. Its variable combinations of cutaneous, muscular, and systemic features mean that the same visible skin pattern may not represent the same overall disease experience. A careful interpretation therefore needs to account for clinical diversity rather than treating dermatomyositis as a single uniform disorder.
Future Directions
Future progress will likely depend on better ways to classify the diverse forms of dermatomyositis and connect clinical patterns with underlying disease mechanisms. Research may also clarify how skin-predominant and muscle-involving forms should be monitored and treated. More precise approaches could help address the limitations created by variable presentation and uncertain disease trajectories.
Systemic Challenges
Dermatomyositis can involve more than the skin and muscles. Sources describe patients with skin disease alone, concomitant muscle disease, or extracutaneous manifestations such as pulmonary disease and associated malignancy. Characteristic skin disease may precede or parallel muscle involvement and can signal risks including interstitial lung disease and malignancy, underscoring the need for multisystem evaluation.
Living With Variable Disease
The effects of dermatomyositis can differ substantially from one person to another. Some people experience primarily skin disease, while others develop muscle weakness or additional pulmonary and systemic problems. This variability can make the condition difficult to recognize and may require ongoing attention to changes beyond visible skin symptoms.