
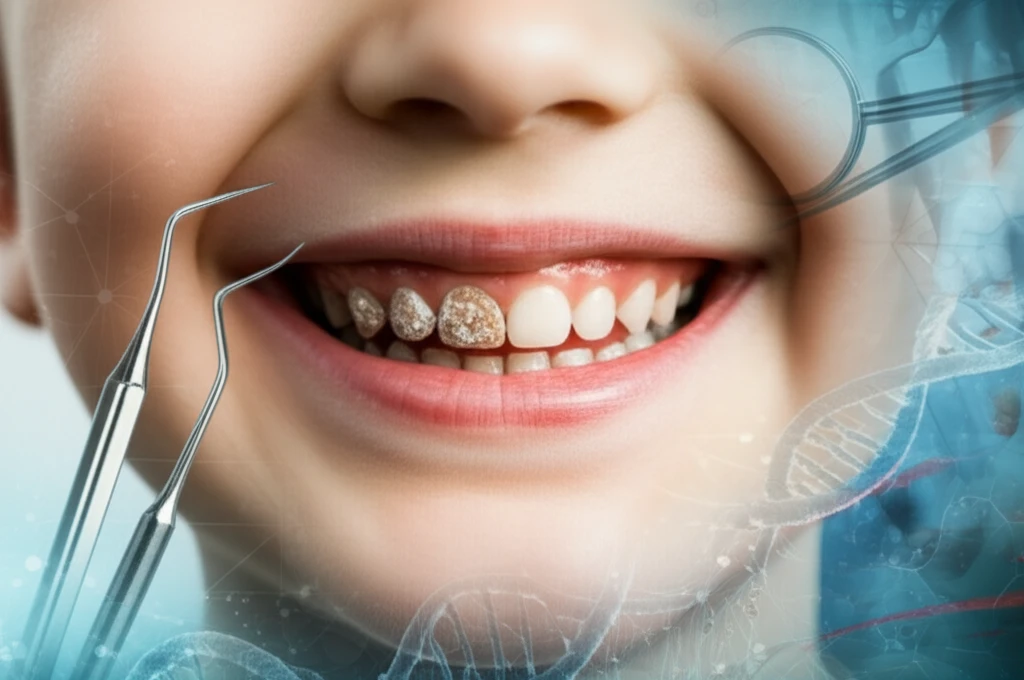
MIH Enamel: Unlocking the Secrets to Stronger Teeth

"A comprehensive look at molar-incisor hypomineralization, its impact on enamel, and what you can do to protect your child's smile."
Imagine your child's permanent teeth emerging, not with a brilliant, strong sheen, but with chalky, discolored patches. This is the reality for many children affected by molar-incisor hypomineralization (MIH), a condition where the enamel, the tooth's protective shield, doesn't develop properly. MIH can make teeth more susceptible to cavities, sensitive to temperature, and even prone to crumbling. Understanding this condition is crucial for parents and caregivers.
MIH, first defined in 2001, is a qualitative developmental defect that affects at least one permanent molar and may involve the incisors. While the exact cause remains elusive, research points to a multifactorial pathogenesis, potentially involving genetic components. The prevalence is significant, ranging from 3% to 22% in Europe and even higher in other parts of the world, making it a common concern for dental professionals.
This article dives deep into the structural, mechanical, and chemical changes associated with MIH-affected enamel, drawing upon a comprehensive review of existing research. We'll explore how MIH impacts tooth structure, what treatments are available, and provide actionable insights to help you protect your child's dental health and overall well-being.
Prevalence and Clinical Impact
A 2025 analysis of 135 studies from 53 countries estimated MIH prevalence at 15.5%, with individual estimates ranging from 0.6% to 46.6%. A separate 2021 meta-analysis estimated prevalence at 13.5% and reported that 36.3% of cases were moderate to severe. In a 2018 study of 1,511 children, MIH was observed in 215 children, or 14.2%, including 9.9% of 8-year-olds and 18.2% of 11-year-olds. The American Academy of Pediatric Dentistry describes MIH as a qualitative enamel defect linked to inadequate mineralization.
Diagnosis and Treatment Challenges
MIH commonly appears as distinct enamel opacities ranging from white to yellow-brown discoloration, and clinical examination should be performed on clean, wet teeth. The condition is assessed using clinical criteria such as ICDAS, while treatment planning depends on its severity and presentation. Reviews describe increased caries risk and note that orthodontic bonding to MIH-affected teeth may require specialized techniques and longer treatment considerations. Because MIH is a qualitative enamel defect caused by inadequate mineralization, conventional approaches may not address the altered enamel structure uniformly.
Defining MIH
MIH was introduced as a term for enamel defects affecting the first permanent molars with involvement of one or more incisors. This pattern distinguishes the condition by combining molar involvement with possible permanent incisor changes. Later descriptions continue to characterize MIH as a developmental enamel defect affecting one or more first permanent molars and sometimes the permanent incisors. Unlike dental caries, MIH is described as a defect in enamel formation rather than a disease caused by caries activity.
What's Happening Inside MIH-Affected Teeth?
Recent research has shed light on the specific alterations that occur in enamel affected by MIH. These changes impact the enamel's strength, appearance, and overall health. A systematic review of 23 studies provides clear evidence of these structural differences.
- Reduced Mineral Content: MIH enamel contains less calcium and phosphorus, the building blocks of strong teeth.
- Increased Porosity: The enamel becomes more porous, making it vulnerable to bacteria and decay.
- Higher Protein Content: MIH enamel has a higher protein concentration compared to healthy enamel, disrupting the mineralization process.
- Structural Changes: Crystals within the enamel are less organized, with loosely packed crystals and wider spaces between them.
- Increased Carbonate Levels: There's an elevated presence of carbon and carbonate, further weakening the enamel structure.
What Recent Reviews Show
An umbrella review defines MIH as a qualitative enamel defect involving the mineralization and maturation of permanent first molars and incisors. A 2023 systematic review reported a correlation between MIH and dental caries across the studies it analyzed. Together, these reviews frame MIH as both a developmental enamel problem and a condition associated with caries occurrence. The evidence summarizes patterns across published studies rather than establishing a single cause for every affected tooth.
Limits of Current Understanding
MIH does not present identically in every child, and its visible severity and clinical consequences can vary. This variability means that a single explanation or treatment pathway may not apply to all cases. Current discussions should therefore distinguish established clinical descriptions from areas where evidence remains incomplete. Further research may be needed to clarify why outcomes differ among affected teeth and patients.
MIH Versus Other Enamel Defects
Dental literature distinguishes enamel hypomineralization from enamel hypoplasia, documenting differences between the two conditions. MIH is characterized by altered enamel quality, whereas the comparison with hypoplasia concerns a different type of enamel defect. Compared with healthy enamel, affected molars have been reported to carry a 10-fold higher risk of developing caries. The reported increase is associated with the high porosity of enamel affected by MIH.
Taking Control of MIH: What Can You Do?
While MIH presents challenges, it's important to remember that proactive management can significantly improve outcomes. Here's what you can do:
A Distinct Enamel Pattern
MIH is used to describe a special pattern of enamel defects affecting permanent molars and often incisors. The terminology was first used by Weerheijm and colleagues. This naming milestone helped distinguish the characteristic distribution of the defect from other enamel abnormalities. The definition provides a foundation for consistent recognition and scoring in clinical settings.
Toward Structured Care
A 2016 review presented current knowledge about MIH and proposed therapeutic options. It also described a clinical approach to management after diagnosis according to a protocol. This direction emphasizes organized assessment and treatment planning rather than relying on a single intervention for every presentation. Future clinical progress may build on diagnostic protocols that connect the identified pattern and severity with appropriate care.
Care Beyond the Enamel
MIH can create challenges that extend beyond identifying a visible enamel defect. Differences in severity and presentation may complicate consistent diagnosis, treatment planning, and long-term monitoring. These challenges suggest a need for coordinated clinical assessment and clear communication with families. The available material does not establish a single systemic explanation or universal solution.
Children Living With MIH
A clinical video source reports that MIH may affect as many as 20% to 40% of children with newly erupted teeth. MIH is also described as affecting permanent first molars and often being associated with similarly affected incisors. A case report involving monozygotic twins illustrates how MIH can appear in real clinical management alongside hypodontia. These presentations help explain why care may need to be individualized for each child.
Early Detection: Regular dental check-ups are essential for early diagnosis. Dentists can identify MIH even before significant damage occurs. Protective Measures: Fluoride treatments, sealants, and special toothpastes can help strengthen the enamel and prevent decay. Dietary Changes: Limiting sugary drinks and snacks reduces the risk of acid attacks that further erode weakened enamel. Restorative Treatments: When damage occurs, fillings, crowns, or other restorations can protect and restore affected teeth. Remember, each child's case is unique, and treatment plans should be individualized.
By staying informed, working closely with your dentist, and adopting preventive strategies, you can help your child maintain a healthy, confident smile despite the challenges of MIH. The future of dental care involves understanding these conditions and providing personalized, effective solutions. Early intervention is key!