
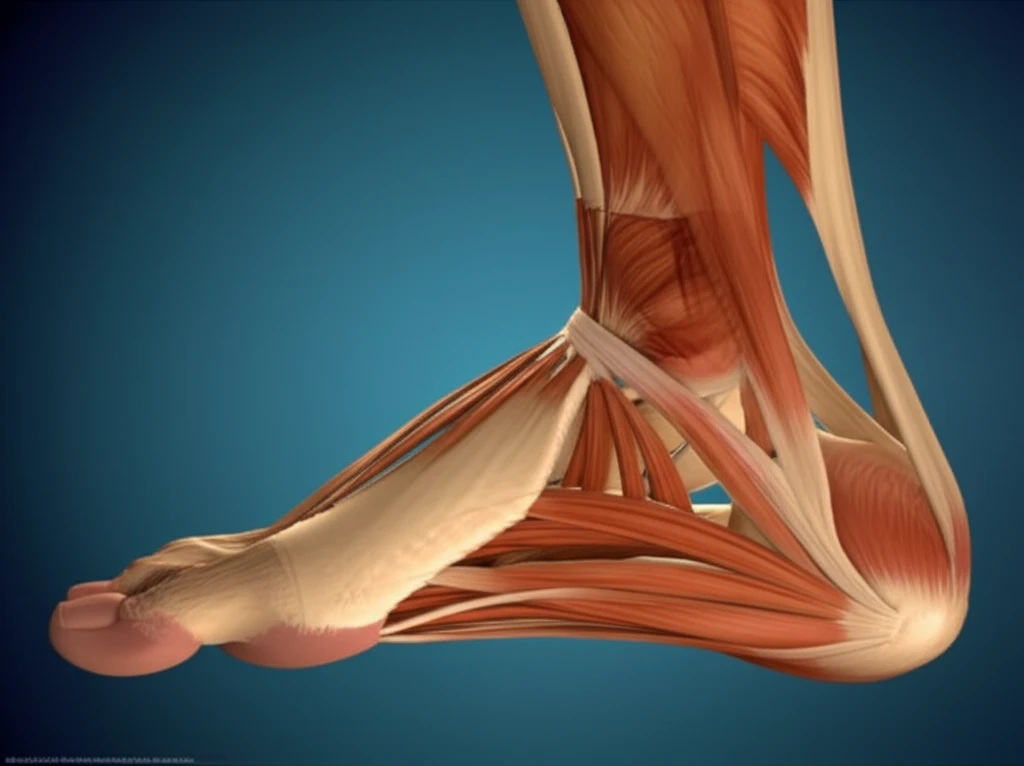
Illustration showing the connection between a tight calf muscle and foot pain.

Tight Calves, Achy Feet? Unveiling the Hidden Link Between Calf Tightness and Foot Pain

"Discover how tight calf muscles could be the surprising culprit behind your foot and ankle problems and what you can do about it."


Do you suffer from persistent foot pain, plantar fasciitis, or other frustrating foot and ankle problems? The solution might be higher up than you think – in your calf muscles. Gastrocnemius tightness (GT), or tightness in the calf muscles, is increasingly recognized as a contributing factor to various musculoskeletal issues, especially those affecting the lower extremities.

While treatments for foot and ankle pain often focus on the affected area, addressing calf tightness can be a game-changer. Many experts believe that tight calf muscles predispose individuals to a range of foot and ankle pathologies. This has led to a rise in procedures aimed at lengthening or releasing the gastrocnemius muscle to alleviate these conditions.

But how common is GT, really? And how does it differ between people with foot and ankle problems versus those without? A recent population-based study investigated the incidence and severity of GT in patients with foot and ankle pathology (FAP), shedding light on this often-overlooked connection.

AI Search Multiple angles on this topic

How Calf Tightness Affects the Foot

Tight calf muscles can cause pain and problems downstream in the foot and ankle without the connection being obvious. Research published in Scientific Reports identified an initial stiffness cut-off point of 29.08 kPa for the medial gastrocnemius when the ankle was relaxed in people with plantar fasciitis. Another study reports that calf tightness can affect balance and mobility by influencing static and dynamic movement.

Stretching and Clinical Assessment

Calf stretching and plantar fascia-specific stretching are two techniques commonly administered by health care providers for plantar fasciitis. Clinicians describe calf tightness as stiffness, pulling, or reduced flexibility in the back of the lower leg, assessed through a patient history and physical examination rather than as a standalone diagnosis. Clinical guidance also recommends manual therapy, including joint and soft-tissue mobilization, when relevant lower-extremity mobility or calf-flexibility deficits are present.

The Connected Tissue Chain

The calf muscles, Achilles tendon, and plantar fascia form a connected chain of tissue extending from the back of the knee toward the toes. The gastrocnemius and soleus connect to the foot through the Achilles tendon, helping explain why calf tightness may be associated with foot or heel pain. However, calf tightness can have causes ranging from overuse to serious conditions such as deep vein thrombosis, especially when swelling, redness, warmth, sudden severe pain, or numbness is present.

The Calf-Foot Connection: What the Research Reveals

Illustration showing the connection between a tight calf muscle and foot pain.

Researchers conducted a prospective study, comparing GT in patients diagnosed with FAP to a control group matched for age, gender, and ethnicity. The FAP group consisted of individuals seeking treatment at a Foot & Ankle unit, while the control group comprised healthy adult volunteers. To ensure accurate results, individuals with previous surgery, Achilles tendon issues, or ankle arthritis were excluded from the study.

GT was measured using a digital inclinometer during the lunge test. This involved calculating the difference in maximal ankle dorsiflexion (the ability to point your toes upwards) with the knee extended versus flexed. Data collection for the control group occurred first, and a subsequent power calculation determined that a FAP cohort size of 91 feet would be sufficient to detect a clinically significant 2-degree difference in GT.

Here's a breakdown of the key findings:
  • Increased GT in FAP Patients: The study revealed that individuals with foot and ankle pathology demonstrated significantly greater GT compared to the control group (8.0° vs 6.0°).
  • Forefoot Pathology Matters: Subgroup analysis highlighted an even more pronounced difference in patients with forefoot pathology (e.g., bunions, hammertoe), who exhibited a mean GT of 10.3°.
  • Not Always a Factor: Interestingly, when comparing patients without forefoot pathology to the control group, no significant difference in GT was observed.
  • Significant Tightness Prevalence: Over 20% of FAP patients and nearly 40% of those with forefoot issues had GT exceeding two standard deviations above the control group mean.
AI Search Multiple angles on this topic

Why Tightness Is Not the Whole Explanation

Severe limitations in ankle dorsiflexion have been associated in the literature with pathological foot deformities, altered gait, and reduced functional performance. But evidence about treatment outcomes has limitations: a six-year study comparing proximal medial gastrocnemius recession and stretching with stretching alone identified its small study population as a major limitation. These findings caution against treating calf tightness as a complete explanation for every case of foot pain or assuming that one intervention will work uniformly.

Mobility and Recovery Options

Limited ankle mobility caused by calf tightness can alter walking mechanics and may contribute to pain in the front of the foot, including metatarsalgia. Calf tightness is also associated with conditions such as shin splints, Achilles tendinitis, plantar fasciitis, and muscle or joint sprains. A calf stretcher board and a traditional foam roller are presented as different recovery tools for tight calves and plantar fasciitis, but the source material does not establish that one is superior.

These results suggest that increased GT is indeed more prevalent in the FAP population. However, the link appears strongest in those with forefoot problems. This indicates that calf tightness may play a more critical role in certain types of foot and ankle conditions.

What Does This Mean for You?

If you're struggling with foot or ankle pain, especially if you have forefoot issues, it's worth exploring whether calf tightness is a contributing factor. While not all foot and ankle problems stem from tight calves, it's reasonably common, especially in those with forefoot pathology. Consult with a healthcare professional to assess your GT and determine the best course of action. Further research is needed to determine the specific degree of GT that is considered clinically significant and which patients are most likely to benefit from interventions targeting calf tightness, such as stretching or, in some cases, surgical release.

AI Search Multiple angles on this topic

Restoring Ankle Dorsiflexion

A systematic review and meta-analysis found some evidence that static stretching can improve ankle-joint dorsiflexion range of motion. The review also reported evidence for static stretching combined with ultrasound, diathermy, diathermy and ice, heel-raise exercises, superficial moist heat, and warm-up activities. Reported standardized mean differences varied by intervention, including 0.70 to 1.69 for static stretching alone and 0.70 to 0.77 for heel-raise exercises.

Treatment in Practice

A registered clinical trial is examining Rolfing Soft Tissue Manipulation and the Bowen Technique as potential manual therapies for calf tightness that limits ankle dorsiflexion. In a recreational runner case study, training load, strength, mobility, massage, and reassessment were used to understand recurring symptoms during running. Another case report used a NEUBIE NMES device alongside sustained low-load stretching, instrument-assisted soft-tissue mobilization, and exercises aimed at improving heel-toe walking and dorsiflexion strength.

How isolated calf tightness differed from healthy controls

  • approximately 55% of the study populationUsing an ankle dorsiflexion threshold of 5° or less, approximately 55% of the study population met the definition of gastrocnemius tightness.[1]
  • 0.21° versus 19.14° active ankle dorsiflexionChildren with isolated gastrocnemius tightness had markedly less active ankle dorsiflexion with the knee extended than healthy controls: 0.21° versus 19.14°. The reported effect size was very large.[1]
  • 8.16 versus 10.76; 8.71 versus 11.42 kgfLower muscle strength was also observed in selected muscle groups. Iliopsoas strength was 8.16 versus 10.76 kgf on the right, while gluteus maximus strength was 8.71 versus 11.42 kgf on the left.[1]

What the measured differences represent

The evidence places isolated gastrocnemius tightness within a broader comparison of foot posture, ankle mobility, muscle strength, jumping, and postural control. These were proposed domains of difference relative to peers without isolated tightness, not evidence that every domain was impaired in every child.[1]

The assessment used the Foot Posture Index and a handheld dynamometer, so the reported findings combine foot-position measurements with instrument-based strength testing rather than relying on a single clinical observation.[1]

What remains uncertain about calf tightness in children

  • The clinical relevance of isolated gastrocnemius tightness in children remains unresolved. A measurable difference from healthy controls does not by itself establish that tightness causes pain, disability, or later foot deformity.[1]
  • The evidence does not establish whether gastrocnemius tightness is an abnormal finding in children, because recurrent leg pain has also been reported in this population.[1]
  • Adult evidence linking severe dorsiflexion restriction with foot deformity, gait changes, and reduced function cannot by itself determine the importance of the smaller-child findings described here.[1]
  • Limited dorsiflexion is described as capable of producing compensatory movements and increasing stress on the lower limb, but this mechanism does not establish which movement changes occurred in the measured children or how clinically important they were.[1]

About this Article -

Written with AI assistance from published research, and reviewed by the Mystum team. See our About page for more information.

Everything You Need To Know

1

What is gastrocnemius tightness and why is it important?

Gastrocnemius tightness, or GT, refers to the tightness in the calf muscles. This condition is significant because it's increasingly recognized as a contributing factor to musculoskeletal issues, particularly those affecting the lower extremities, such as foot and ankle problems. If left unaddressed, GT can predispose individuals to various foot and ankle pathologies, potentially leading to chronic pain and discomfort. The implications of GT extend to treatment strategies, as addressing calf tightness can be a game-changer when treatments for foot and ankle pain often focus on the affected area. Procedures aimed at lengthening or releasing the gastrocnemius muscle are being considered to alleviate these conditions.

2

How was gastrocnemius tightness measured in the study, and why is that significant?

The study utilized a digital inclinometer during the lunge test to measure Gastrocnemius tightness (GT). The lunge test involved calculating the difference in maximal ankle dorsiflexion (the ability to point your toes upwards) with the knee extended versus flexed. The significance of this measurement technique lies in its ability to quantify the degree of calf tightness objectively. Implications of this method is the understanding of the correlation between the quantified degree of tightness and foot and ankle health.

3

What did the research reveal about the connection between gastrocnemius tightness and foot and ankle problems?

The research revealed that individuals with foot and ankle pathology (FAP) exhibited significantly greater Gastrocnemius tightness compared to the control group. Specifically, those with forefoot pathology, such as bunions or hammertoe, showed an even more pronounced difference in GT. This is important because it highlights a strong link between calf tightness and certain types of foot and ankle conditions, especially those affecting the forefoot. However, it's also important to note that not all foot and ankle problems stem from tight calves, and GT was not significantly different in patients without forefoot pathology compared to the control group. The implication is that treatments targeting calf tightness may be most effective for individuals with forefoot issues.

4

If I have foot or ankle pain, should I be concerned about gastrocnemius tightness?

If you are experiencing foot or ankle pain, especially if you have forefoot issues, it is worth considering whether Gastrocnemius tightness (GT) is a contributing factor. Consult with a healthcare professional to assess your GT and determine the best course of action. This is significant because addressing calf tightness through interventions like stretching or, in some cases, surgical release, may alleviate your foot and ankle problems. The implication is that managing GT could improve your quality of life by reducing pain and improving mobility. Additional things to consider include other potential factors contributing to foot and ankle pain should also be evaluated.

5

What further research is needed regarding gastrocnemius tightness?

Further research is needed to determine the specific degree of Gastrocnemius tightness (GT) that is considered clinically significant and which patients are most likely to benefit from interventions targeting calf tightness. This is important because it will help healthcare professionals tailor treatment plans to individual patients and ensure that interventions are targeted where they will be most effective. The implications of this research include the development of more precise diagnostic criteria and treatment protocols for GT-related foot and ankle problems.

Newsletter Subscribe

Subscribe to get the latest articles and insights directly in your inbox.