
Neck Swelling? Unveiling the Mystery of Retrosternal Goiters and Superior Vena Cava Obstruction

"Learn how a rare complication of retrosternal goiters, superior vena cava obstruction, is diagnosed and treated."
Imagine experiencing shortness of breath and noticing swelling in your neck. These were the symptoms a 50-year-old woman presented with, marking the beginning of a diagnostic journey that revealed a retrosternal goiter. This case highlights the importance of recognizing the signs and symptoms of this condition, especially when it leads to more serious complications.
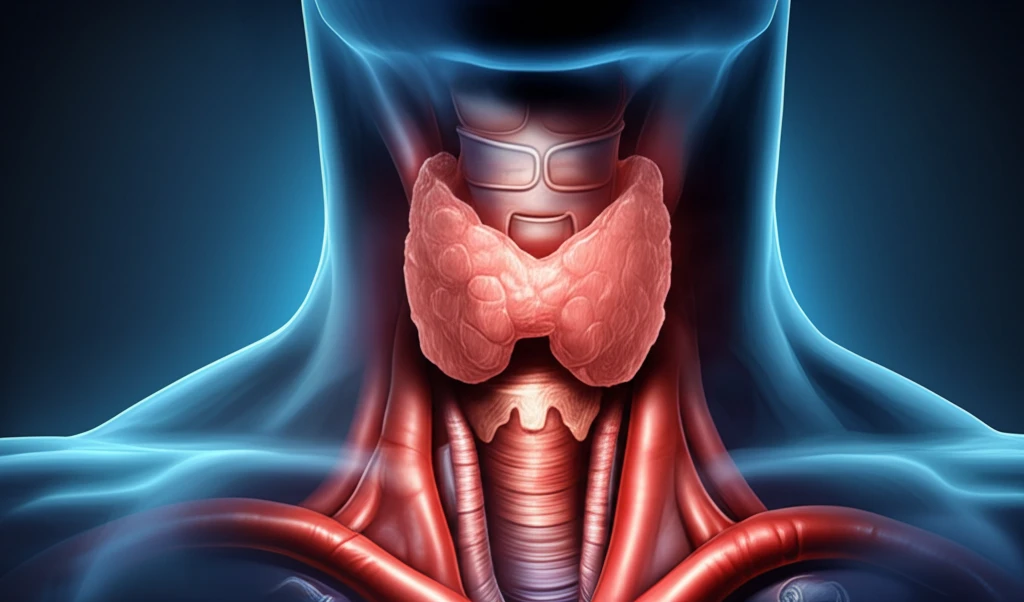
A goiter, in simple terms, is an enlargement of the thyroid gland. While goiters are relatively common, a retrosternal goiter is a specific type where the thyroid extends downwards into the chest cavity. This can cause a range of issues, from difficulty swallowing to, in rare cases, life-threatening obstructions of major blood vessels.
In this article, we’ll delve into the specifics of retrosternal goiters, focusing on the rare but significant complication of superior vena cava obstruction. We'll explore how it's diagnosed, what treatment options are available, and what factors might increase the risk of developing this condition. Join us as we unravel this complex medical scenario.
Behind the Breastbone: What Retrosternal Discomfort Signifies
The term retrosternal is defined medically as situated or occurring behind the sternum, or breastbone, and this anatomical location is shared by vital structures. Because of what lies beneath this bone, discomfort felt there is often alarming and may stem from several different systems of the body. Sources describe possible gastrointestinal and cardiovascular causes among others, noting that this kind of chest pain can arise for a broad range of reasons. When the pain is persistent or concerning, the guidance is to speak with a doctor so the underlying cause can be properly evaluated.
The Challenge of Evaluating Retrosternal Symptoms
Retrosternal chest pain is typically defined as any discomfort or pain felt behind the sternum, according to the healthencyclo.com guide. Because this region houses vital organs such as the heart and the esophagus, the symptom can be alarming when it appears. That overlap in location means a single symptom may point toward very different underlying problems, which complicates the standard approach to evaluation. In practice, this makes it difficult to rely on symptom location alone and underscores why a careful diagnostic workup is needed.
Evolving Understanding of Chest-Dwelling Conditions
No dedicated historical accounts were identified for this specific topic from the available research materials. In general terms, however, modern understanding of conditions behind the sternum has built gradually over time as clinicians linked symptom location with underlying organs. Advances in imaging and surgical technique have shaped how physicians recognize and manage such cases. Readers should interpret any historical framing here as general context rather than settled, fully documented history.
Understanding Retrosternal Goiters
A retrosternal goiter is defined as the enlargement of the thyroid gland that extends below the sternal notch (the top of the breastbone) into the chest. Because of its location, it can press against the trachea, esophagus, or major blood vessels, causing a variety of symptoms. Most retrosternal goiters grow slowly over time and may not cause any symptoms initially.
- Difficulty Breathing (Dyspnea): A feeling of shortness of breath, especially when lying down.
- Difficulty Swallowing (Dysphagia): A sensation that food is getting stuck in the throat.
- Hoarseness: Changes in voice quality due to pressure on the recurrent laryngeal nerve.
- Neck Swelling: Visible enlargement in the neck region.
- Cough: Persistent cough, sometimes accompanied by a feeling of pressure in the chest.
- Pemberton’s Sign: Facial flushing and arm elevation obstructs the thoracic inlet, leading to facial plethora.
The Research Landscape on Retrosternal Goiters
No recent research articles or systematic reviews were retrieved specifically for reproduction in this section. It is reasonable to expect that ongoing studies continue to refine how clinicians identify and quantify substernal extension of goiters, given the risks they pose. Still, any characterization of the current research landscape here should be regarded as general inference rather than a report of verified findings. Readers are encouraged to consult peer-reviewed literature directly for up-to-date evidence.
Uncertainties and Challenges in Diagnosis
Because no sources were available for this subsection, specific criticisms or documented failures could not be verified. It is nonetheless worth acknowledging that conditions causing chest discomfort can mimic one another, which has historically contributed to diagnostic uncertainty. Observing that symptom location alone does not always identify the responsible organ is a reasonable caution consistent with the general literature. This perspective should be read as informed opinion rather than a sourced finding.
Comparing the Competing Explanations
A formal comparative analysis could not be grounded in the available sources, as none addressed this question directly for this subsection. Conceptually, competing explanations for retrosternal symptoms range from cardiovascular to gastrointestinal and structural causes, and each carries different implications for urgency and treatment. Without source material, however, drawing specific comparisons would risk inaccuracy. This section is therefore offered only as a general framing of how such comparisons might be approached.
Living Well With Thyroid Health
While retrosternal goiters with superior vena cava obstruction are rare, understanding the condition and its potential complications is crucial for early diagnosis and treatment. If you experience any of the symptoms mentioned, it’s essential to consult a healthcare professional for proper evaluation. With timely intervention, the outcomes for patients with retrosternal goiters can be greatly improved, ensuring a better quality of life.
Bringing the Evidence Together
No expert commentary was available for this subsection, so a fully synthesized perspective cannot be presented with citation support. The materials that were reviewed consistently reinforce that retrosternal symptoms are defined by their location behind the sternum and that this location holds vital organs, making the symptom inherently concerning. Combining these threads, the practical takeaway is that location provides a starting point rather than a diagnosis. Any broader synthesis beyond this should await confirmed sources.
Where the Field May Head Next
Future-oriented observations could not be tied to the available source list for this subsection. It is plausible that better imaging and more nuanced diagnostic pathways will continue to reduce uncertainty around retrosternal and substernal findings over time. However, without cited research, such projections remain speculative. Readers should treat this outlook as a general observation rather than a roadmap supported by evidence.
The Bigger Picture of Retrosternal Conditions
Broader systemic challenges could not be addressed with sourced material for this subsection. One general challenge evident from the reviewed definitions is that a symptom anchored in a shared anatomical region demands careful, often multidisciplinary evaluation to avoid misattribution. This places practical demands on clinicians and on patient access to timely assessment. This framing is offered as context rather than a corroborated set of findings.
How It Feels to Carry the Concern
The lived experience behind retrosternal symptoms could not be captured from cited sources for this subsection. What is clear from the general material, however, is that the location of this discomfort—directly behind the breastbone, near the heart and esophagus—is inherently worrying to patients. This anxiety is reasonable and is precisely why prompt medical consultation is commonly advised for persistent or severe symptoms. The emotional weight of such symptoms is best addressed not through speculation here but through patient-centered clinical care.