
Is Late-Onset Crohn's Different? Understanding the Risks

"New research sheds light on how Crohn's disease manifests differently depending on when it starts, influencing potential complications and treatment strategies."
Crohn's disease, a chronic inflammatory condition of the digestive tract, doesn't always manifest in the same way. Research increasingly suggests that the age at which Crohn's disease begins can significantly influence its characteristics and potential complications. This article explores the key differences between early-onset and late-onset Crohn's disease, drawing on recent research to highlight the unique risks associated with the latter.
Understanding these differences is crucial for both patients and healthcare providers. By recognizing the distinct patterns of late-onset Crohn's, medical professionals can tailor diagnostic and treatment approaches to optimize patient outcomes. For individuals experiencing symptoms later in life, awareness of these nuances can empower them to seek timely and appropriate care.
This article will delve into a study comparing the clinical features of early-onset versus late-onset Crohn's disease, focusing specifically on the risk of intestinal perforation and perianal fistula. We will break down the findings in an accessible way, providing clear insights into how age of onset impacts the disease course and management strategies.
How Common Is Late-Onset Crohn’s?
The CDC estimates that 2.4 to 3.1 million people in the United States live with inflammatory bowel disease, and reports that prevalence and health care costs are rising. Crohn’s disease most commonly begins between the second and fourth decades of life, but approximately 10% to 20% of individuals develop late-onset disease, often defined as diagnosis after age 60. Late-onset Crohn’s remains less well characterized than adult-onset Crohn’s, prompting research comparing disease characteristics and potential risk factors at diagnosis.
Diagnosis Can Be More Complicated With Age
Late-onset Crohn’s is less well characterized than adult-onset Crohn’s, so comparisons at diagnosis remain an important research focus. A 2018 study identified a late-onset subgroup defined as diagnosis at age 55 or older and reported significantly lower polygenic risk scores than in an intermediate-onset group diagnosed between ages 5 and 55. Symptoms may also be less typical in older adults; one cited comparison found that older adults with ulcerative colitis had less diarrhea, abdominal pain, and weight loss than younger adults, illustrating why symptom-based recognition may be limited.
Learning From Pediatric Research
One important milestone in Crohn’s research was the launch of the Pediatric RISK Stratification Study by the Crohn’s & Colitis Foundation. The study followed the largest group of pediatric patients in Crohn’s disease history from the time of diagnosis. It identified biomarkers that could predict disease course and severity in children at diagnosis, establishing a foundation for risk-stratification research even though the study focused on pediatric disease.
Late-Onset Crohn's: Higher Risk of Intestinal Perforation
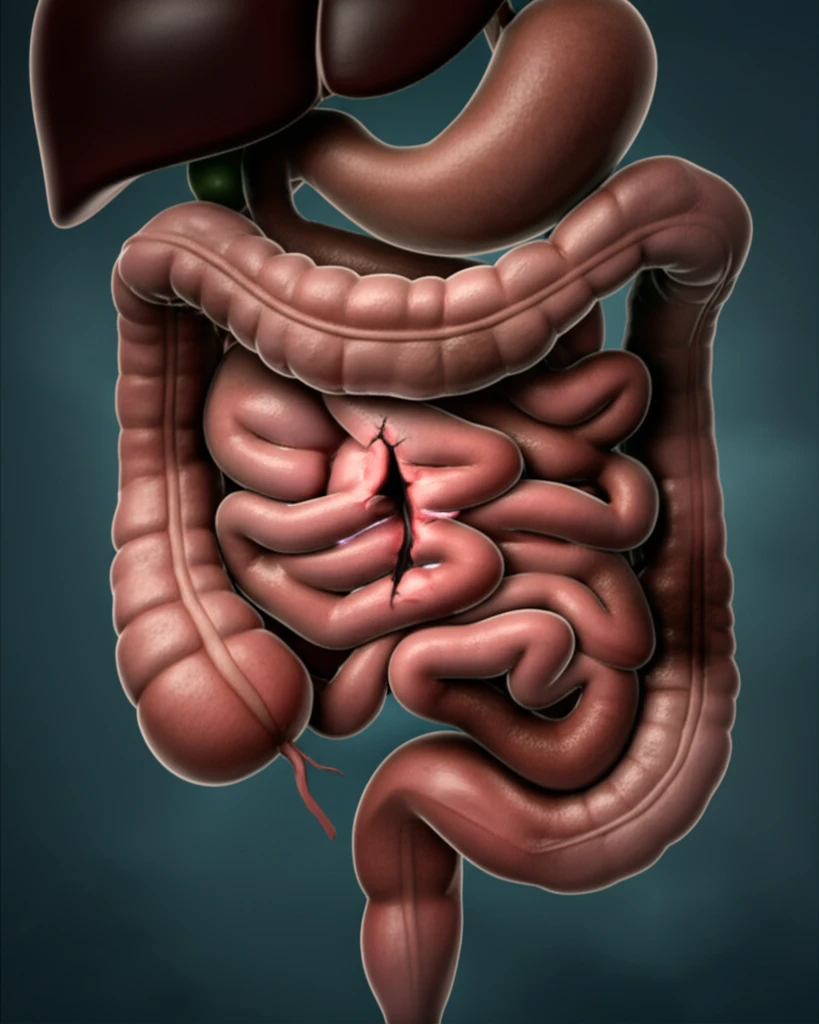
A recent study investigated the differences between early-onset (diagnosis before age 40) and late-onset (diagnosis at age 40 or later) Crohn's disease, utilizing data from the CONNECT cohort. The research revealed a significant trend: patients with late-onset Crohn's disease face a higher risk of intestinal perforation compared to those diagnosed earlier in life.
- Increased Surgical Intervention: Late-onset Crohn's patients underwent abdominal surgery more frequently (33.0%) than their early-onset counterparts (25.0%).
- Elevated Intestinal Perforation Risk: The multivariable analysis showed that late-onset Crohn's disease had an odds ratio of 3.090 (95% CI: 1.228-7.772, p=0.017) for intestinal perforation. This indicates a statistically significant higher risk.
An Emerging Research Area
Late-onset Crohn’s remains an emerging area of research rather than a fully settled clinical category. Current work is examining whether patients diagnosed later in life have distinct disease characteristics and risk factors compared with those diagnosed earlier. Because the available evidence is still developing, conclusions about how consistently late-onset disease differs should be treated as provisional.
Limits of Current Understanding
The evidence base does not yet provide a complete or uniform picture of late-onset Crohn’s disease. The condition is less well characterized than adult-onset Crohn’s, and symptoms in older adults may be less typical, potentially making recognition more difficult. These limitations support caution against assuming that every older patient will follow the same clinical pattern.
A Potentially Distinct Subgroup
Research has suggested that late-onset Crohn’s may represent a subgroup with biological differences from earlier-onset disease. A 2018 study reported lower anti-CBir1 levels and much lower ASCA levels in late-onset disease, which the authors linked to shifted genetic and environmental factors, altered immune responses, and different clinical phenotypes. The same research identified a late-onset group with significantly lower polygenic risk scores, although these findings do not establish that every late-onset case follows a separate disease pathway.
Key Takeaways and Implications
The research highlights a crucial distinction in Crohn's disease presentation based on age of onset. Late-onset Crohn's disease appears to be associated with a higher risk of intestinal perforation, necessitating careful monitoring and potentially more aggressive management strategies.
Recognizing Warning Signs
Late-onset inflammatory bowel disease warrants attention when new, persistent gastrointestinal symptoms develop in an older adult. The available expert guidance emphasizes not ignoring possible warning signs and seeking medical advice. This is particularly important because late-onset disease may not present in exactly the same way as disease recognized earlier in life.
Earlier Diagnosis as a Research Priority
Current Crohn’s research continues to focus on challenges, future directions, and ways to improve care. A major priority identified in the reviewed literature is earlier diagnosis, because it is often crucial for preventing complicated Crohn’s disease. For late-onset patients, future work may help clarify which clinical or biological signals can support faster and more accurate recognition.
A Complex Care Context
Late-onset Crohn’s care takes place within a broader health system that must distinguish new inflammatory bowel symptoms from other conditions common in later life. Because the research base is still developing, clinicians may need to account for variation in presentation and avoid relying on a single symptom pattern. More consistent evidence could help reduce uncertainty in diagnosis and care planning.
Symptoms and Treatment in Real Life
Reported clinical features of late-onset Crohn’s ileitis can include abdominal cramps, fever, weight loss, anemia, and intractable diarrhea. One case involved an elderly Indian man who was initially diagnosed with irritable bowel syndrome before presenting with diarrhea, anorexia, and weight loss for about a month. Separately, a 2025 study evaluated real-world treatment patterns among pediatric and adult patients with Crohn’s disease using a large U.S. administrative claims database over one- and three-year follow-up periods.
For individuals diagnosed with Crohn's disease later in life, it's essential to be aware of this increased risk and to discuss preventive measures and early warning signs with their healthcare provider. Prompt attention to symptoms and proactive management can significantly improve outcomes.
Further research is warranted to explore the underlying causes of these differences and to develop targeted therapies that address the specific challenges of late-onset Crohn's disease. Understanding the nuances of Crohn's presentation across different age groups is key to optimizing patient care and improving long-term outcomes.