
Breathe Easier: New Hope for Asthma and Chronic Sinusitis Sufferers

"Could a simple nasal exhalation technique unlock better relief?"
If you're among the millions battling both asthma and chronic rhinosinusitis, you know the struggle is real. Eosinophilic chronic rhinosinusitis (ECRS), a particularly stubborn type of sinus inflammation, often goes hand-in-hand with asthma, creating a frustrating cycle of airway woes. Traditional treatments sometimes fall short, leaving many searching for better solutions.
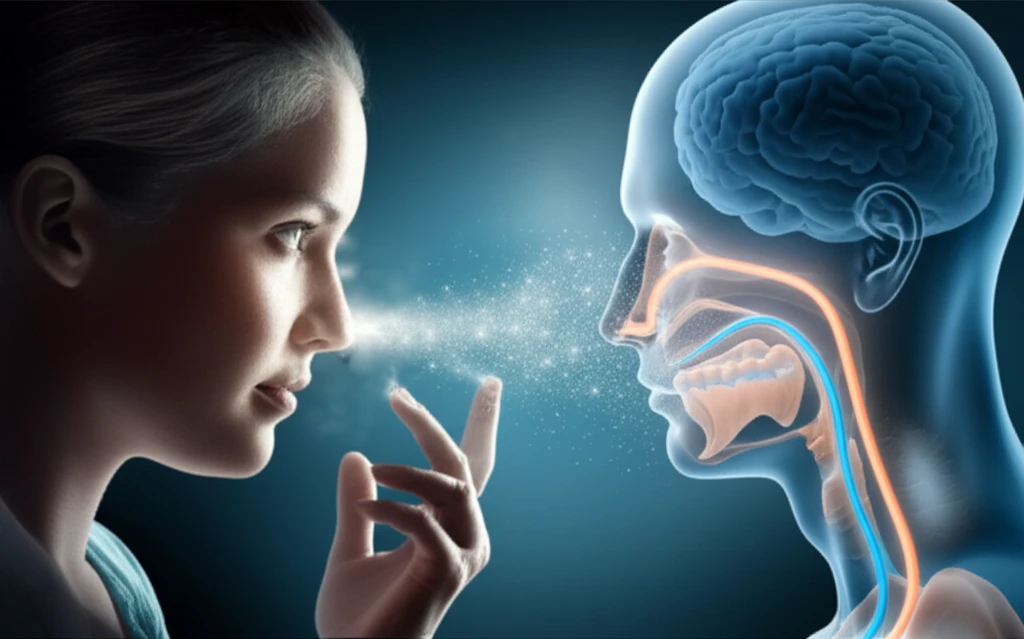
Now, a new study offers a glimmer of hope. Researchers have been exploring a unique method of delivering inhaled corticosteroids (ICS)—a common asthma medication—by exhaling it through the nose. This technique, known as ETN (exhalation through the nose), aims to target inflammation in both the upper and lower airways, addressing the 'united airway' concept that links these conditions.
This article delves into the findings of a recent clinical trial investigating the effectiveness of HFA-BDP (beclomethasone dipropionate) metered-dose inhaler ETN. We'll explore how this approach could potentially improve symptoms, reduce inflammation, and enhance the quality of life for those struggling with ECRS and asthma.
The Asthma–Sinusitis Connection
Asthma and chronic rhinosinusitis are frequently comorbid, although reported rates of severe asthma with chronic rhinosinusitis with nasal polyps vary by study type, size, and location. A 2024 clinical study of 15 patients with chronic rhinosinusitis without nasal polyps and bronchial asthma found that worsening sinus inflammation was associated with deteriorating pulmonary function. Research has also examined asthma–sinusitis relationships through measures including oral corticosteroid use and oxygen saturation.
Treatment Requires Two-Way Management
Asthma and chronic sinusitis involve inflammation in the lower and upper airways, respectively, and their overlapping pathophysiology has led to similar medical-management approaches. However, optimal care for people with chronic rhinosinusitis and asthma may require directed treatment of both conditions because not every sinus intervention changes asthma status. Endoscopic sinus surgery is considered an effective and safe option when standard medical therapy has not provided sufficient benefit, but intranasal corticosteroids may improve sinus symptoms without significantly improving lung function, asthma quality of life, or poorly controlled asthma rates.
From Separate Diseases to Shared Airways
Chronic rhinosinusitis was traditionally classified by duration, with chronic disease defined as symptoms lasting longer than 12 weeks. Over time, researchers recognized that chronic rhinosinusitis and asthma share pathophysiologic mechanisms and can exacerbate one another. The connection also broadened attention to upper-airway conditions such as rhinitis; one reviewed source reports that nearly 80% of people with asthma report some form of rhinitis.
How Does Nasal Exhalation Work?
The study, published in Frontiers in Immunology, involved 23 patients with severe ECRS and asthma whose conditions were not adequately controlled by standard nasal corticosteroids. The participants were divided into two groups: one receiving HFA-BDP via ETN, and the other receiving a placebo inhaler using the same ETN technique. Both groups continued their existing treatments.
- Inhaling fine particles released from a metered-dose inhaler (MDI) orally for 3 seconds using a valved holding chamber.
- Holding breath for 3 seconds.
- Exhaling through the nose for 3 seconds.
A Shift Toward Precision Treatment
Recent reviews describe chronic rhinosinusitis care as moving from conventional symptom-focused treatment toward precision medicine informed by molecular insights. The Italian CHRONOS project has synthesized evidence and expert consensus on long-term biologic treatment for severe chronic rhinosinusitis with nasal polyps. Comparative biologic effectiveness in asthma patients with comorbid chronic rhinosinusitis or nasal polyps remains unclear, indicating that important treatment questions are still unresolved.
Why Improvement Is Not Guaranteed
Treating inflammation in one part of the airway does not necessarily resolve disease throughout the respiratory system. Some patients may experience better nasal or sinus symptoms without corresponding improvement in lung function or asthma control. These limitations suggest that treatment results can vary and that combined conditions may require individualized evaluation rather than reliance on a single intervention.
Shared Biology, Different Outcomes
Asthma and chronic rhinosinusitis with nasal polyps can coexist and may reflect related inflammatory processes, but symptoms and treatment responses are not identical. A 2021 review specifically examined whether biologic agents are equally effective for asthma and sinonasal symptoms in people with both conditions. Patient-facing clinical guidance likewise treats sinusitis and asthma as linked conditions while distinguishing their symptoms, causes, and treatment options.
The Future of Airway Treatment
The study revealed that HFA-BDP MDI ETN led to significant improvements in nasal polyp scores, sinus CT scans, and overall quality of life compared to the placebo group. The ETN group also experienced a reduction in FENO levels and improved sensitivity to corticosteroids, suggesting a decrease in airway inflammation.
The Promise and Limits of Biologics
Patients with several type 2 inflammatory conditions have shown improvements in lung function, radiographic sinusitis, and blood markers of type 2 inflammation after starting biologic therapy compared with controls. At the same time, evidence supports oral and topical medications more strongly for sinus-specific outcomes than for improving lung function or asthma control. Findings that intranasal corticosteroids modestly reduced asthma and sinus symptom scores but did not significantly improve lung function or asthma quality of life underscore the limits of assuming that sinus improvement will automatically translate into better asthma outcomes.
Toward More Targeted Care
Future care will likely continue moving toward treatments selected according to the inflammatory features and clinical pattern of each patient. Biologics and other precision strategies are promising, but their comparative effectiveness for coexisting asthma and chronic rhinosinusitis remains an active research question. Progress will depend on clarifying which therapies improve nasal disease, asthma, or both.
A Whole-Airway Challenge
Chronic rhinosinusitis is a common comorbidity in adults with asthma and is being studied for its effect on long-term asthma outcomes in real-world clinical settings. Evidence indicates that coexistence of the two conditions can impair asthma control. Shared inflammatory pathways, including signaling involving thymic stromal lymphopoietin, interleukin-25, interleukin-33, and type-2 innate lymphoid cells, help explain why upper- and lower-airway disease can remain interconnected.
Living With Two Connected Conditions
For people living with both asthma and chronic sinusitis, symptoms in the nose, sinuses, and lungs can interact and complicate daily disease management. A treatment that eases sinus symptoms may not provide the same degree of relief for breathing or asthma control. This uncertainty makes ongoing, individualized assessment important when patients and clinicians evaluate whether a treatment is helping the full pattern of illness.
This research indicates that exhaling inhaled medication through the nose could be a valuable addition to the treatment arsenal for ECRS and asthma, particularly for those who don't respond well to traditional therapies. The ETN technique helps deliver medication to the sinuses, addressing both upper and lower airway inflammation simultaneously.
While the study's findings are promising, further research is needed to confirm these results in larger, multi-center trials. Nevertheless, this novel approach offers a potential new avenue for managing these chronic conditions and improving the lives of those affected.